Showing posts with label T1DM. Show all posts

Saturday, 28 November 2015

Doctor in the House – Watch Diabetes Not Being Reversed Using Low Carb on BBC, While LCHF'ers Freak Out.

This post is about Doctor in the House – Watch Diabetes Reversed Using Low Carb on BBC, While Old-School Dietitians Freak Out.
The YouTube videos may be gone, but the image lives on!
Available to view in the UK on iPlayer 'till 19.12.15 at https://www.bbc.co.uk/iplayer/episode/b06q6y95/doctor-in-the-house-episode-1

In Dr. Eenfeldt's blog post, he makes some schoolboy errors.

1. T2DM (type 2 diabetes mellitus) Reversed with LCHF (low-carb, high-fat) diet. Uh, nope!
a) Sandeep's HbA1c fell from 9.0 to 7.0, which is an improvement but by no means a reversal, as Dr. Chatterjee agrees in https://twitter.com/drchatterjeeuk/status/669875378568171520.
b) Sandeep has T2DM, not T1DM. See When the only tool in the box is a hammer...
Sandeep's BG (blood glucose) went down on LCHF, but what about his dyseverything elseaemia? *sound of crickets chirping*

2. Old-school dietitians freak out. Uh, nope!
In BDA alarmed by controversial and potentially dangerous advice in BBC’s ‘Doctor in the House’, Dr. Duane Mellor sounds pretty cool, calm & collected (though I expect that he sustained injuries from all of the eyeball rolling, as he had to refute for the umpteenth time yet another load of LCHF bullshit).

3. He plays the Shill Gambit card.

Oh, the comments! In typical echo-chamber fashion, LCHF commenters praise Eenfeldt's flawed points. I wonder how long my comment will stay up for?

My comments on the programme (c/p'ed from Facebook):-
"6 minutes in. I think that Priti is deficient in Magnesium (Mg), from her stress levels, anxiety, headaches and difficulty in getting to sleep. Blood tests are useless, as they don't correlate with Mg stores. Need CSF (cerebrospinal fluid) test (lumbar puncture - very painful).

12 minutes in. Priti's blood test results normal. Sandeep has hypovitaminosis D, which is a cause of IR (insulin resistance, it's what caused mine). This important fact is not mentioned. unsure emoticon See https://www.ajcn.org/content/79/5/820.full.pdf

16 minutes in. Talked about sugar in foods & drinks but ignored the large amount of cheese that Sandeep ate earlier. Cheese is *very* energy-dense. Sandeep has been in positive Energy Balance for *way* too long.

24 minutes in. Priti's getting sugar cravings in the morning. Lack of Magnesium also causes IR & poor BG regulation. See https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4549665/

29 minutes in. HIIT (high-intensity interval training) for Sandeep is good for increasing his IS, but little use for reducing his VAT (visceral adipose tissue). You can't out-run your fork.

33 minutes in. Walking for Priti to lose weight? You can't out-walk your fork. If 1,000 steps takes 10 minutes and burns an extra 40kcals, then 10,000 steps takes 100 minutes and burns an extra 400kcals = one chocolate bar.

33:47 minutes in. Sareena has had a full-time job working indoors for the last year. Less sun exposure = falling Vitamin D3 level = deteriorating immune system, deteriorating mood & deteriorating IS. See https://nigeepoo.blogspot.co.uk/2008/12/vitamin-d.html

I don't think that I can watch much more of this programme!"

followed by:-
"In conclusion:-
1. Anyone who suffers from chronic anxiety is probably deficient in Mg.

2. Anyone who lives in the UK (United Kingdom :-D) and has coloured skin and/or works indoors is probably deficient in Vitamin D3.

3. ~85% of people who have T2DM have excessive VAT. Asians who were skinny in early adulthood have limited SAT (sub-cutaneous adipose tissue) hyperplasia, resulting in small skin-folds but large bellies. A LCHF diet is not suitable for over-fat people with T2DM. It should be a LCLF diet i.e. a low-calorie diet, to deplete over-full cells. Calories count.

4. You can't out-walk/run your fork.

5. Dr Chatterjee has a strong bias. This is not a good trait for someone who's supposed to be practising Evidence Based Medicine."

It's interesting that Priti is fatter than Sandeep, yet Priti doesn't have T2DM and Sandeep does. Priti was most likely fatter than Sandeep in their respective childhoods, for whatever reasons. Priti had more SAT hyperplasia than Sandeep, so she has more storage capacity for dietary fat than Sandeep does. Priti can gain more SAT, which protects her from developing T2DM. Sandeep can't, so he gains VAT, which has limited storage capacity and is more metabolically-active than SAT.

See also Adipocyte Hyperplasia - Good or Bad? and A *very* special dual-fuel car analogy for the human body that I just invented.

Thursday, 25 September 2014

Calcium shift: An interesting hypothesis.

More serendipity! Billy the k left a comment that piqued my curiosity.
From https://www.health-heart.org/acceuil.htm The atheroma 'junk' in the media is cholesterol + calcium in older people.

From Aging and calcium as an environmental factor. (emphasis mine)
"The consequences of calcium deficiency might thus include not only osteoporosis, but also arteriosclerosis and hypertension due to the increase of calcium in the vascular wall, amyotrophic lateral sclerosis and senile dementia due to calcium deposition in the central nervous system, and a decrease in cellular function, because of blunting of the difference in extracellular-intracellular calcium, leading to diabetes mellitus, immune deficiency and others.

I highlighted amyotrophic lateral sclerosis in red, as many Facebook friends have been having buckets of water & ice cubes tipped over themselves to raise money for research into this horrible & ultimately fatal condition.

So, what prevents & reverses migration of calcium from hard tissues to soft tissues?
Clue: It carboxylates osteocalcin in bone matrix Gla proteins. Yes, it's Vitamin K2.

See also Calcium, parathyroids and aging. N.B. 50iu/kg bodyweight/day of Vitamin D3 significantly lowers parathyroid hormone.

Wednesday, 27 August 2014

Wheat, Constipation, Ischaemic Heart Disease, Type 1 Diabetes, Schizophrenia and Autism.

Did you see this coming?
Gliadorphin 7, from https://en.wikipedia.org/wiki/Gliadorphin

The above 7-peptide chain contains 3 molecules of proline (the pentagon with a "N" at one corner), just like:-
Bovine β-casomorphin 7, from https://en.wikipedia.org/wiki/Casomorphin

From Further research for consideration in 'the A2 milk case'.
"Prior to discussion it must be clarified that the hypothetical link between A1 consumption with autism spectrum disorder (ASD) and schizophrenia relates not to the cause of the condition but to the aggravation of symptoms associated with these neurological conditions. More specifically, the hypothesis states that the absorption of food-derived exomorphins such as beta casomorphin 7 (BCM 7) may aggravate symptoms associated with ASD or schizophrenia.

This hypothesis is the basis of 'dietary intervention' that excludes gluten and casein (Knivsberg et al., 2002) from the diet of ASD patients. The former, gluten, has been shown to release gliadamorphin, an exomorphin comparable in opioid activity to BCM-7. A number of laboratories in the United States and Europe offer urine tests, which determine the level of peptides including BCM 7 and other beta casomorphins to serve as an indication of the potential usefulness of dietary intervention in the treatment of ASD patients. One published study reports that a casein- and gluten-free diet was accompanied by improvement in 81% of autistic children within 3 months (Cade et al., 2000)."


According to What is gliadorphin?
"What is gliadorphin? Gliadorphin (also called alpha-gliadin or gluteomorphin) is a substance that resembles morphine. Ordinarily, this is a short-lived by-product from the digestion of gluten molecules (found in wheat, barley, rye, oats, and several other grains). Gliadorphin is very similar to casomorphin. Gliadorphin has been verified by mass spectrometry techniques to be present in unusual quantities in urine samples of children with autism, and are believed by many to be a central part of the system of causes and effects that cause autistic development. The most probable reasons for the presence of these molecules are:
* One or more errors in the breakdown (digestion) process caused by enzyme deficiency and/or
* Abnormal permeability of the gut wall (that would allow these relatively large molecules to enter the bloodstream from the intestine in abnormal quantities)."

Continued on Rheumatoid Arthritis: It's the food!

Sunday, 24 August 2014

Cow's milk, Constipation, Ischaemic Heart Disease & Type 1 Diabetes.

Hat-tip to Jamie Scott and https://twitter.com/_Jamie_Scott/status/503383804686262272 , which led to A1 threat to NZ dairy.
From https://en.wikipedia.org/wiki/Milk

There are a few problems with feeding cow's milk to baby humans.

1. It contains bovine beta casein A1. During digestion, this is broken down into a 7-amino acid peptide chain beta-casomorphin7 (BCM7), which appears to cause issues (e.g. increased gut permeability) increasing the RR of diseases like Type 1 Diabetes and Ischaemic Heart Disease. See https://www.ncbi.nlm.nih.gov/pubmed/?term=A1[All%20Fields]%20AND%20%22beta-casein%22[All%20Fields]%20AND%20%22humans%22[MeSH%20Terms]%20AND%20%28hasabstract[text]%20AND%20%22humans%22[MeSH%20Terms]%29 A solution is to use A2 milk, or goat's milk which is apparently naturally A2. See also Further research for consideration in 'the A2 milk case'.


2. It's much higher in protein (4g/100mL) than human breast milk (1.1g/100mL), as baby cows are supposed to grow very rapidly, unlike baby humans. As 80% of the protein in milk is casein, and casein is joined to calcium as calcium caseinate, this increases the calcium intake, and too much calcium relative to magnesium is constipating. A solution is to increase magnesium intake, or dilute 1 part cow's milk with ~3 parts water & add some coconut oil, to get the fat content back up to 4.4g/100mL.

Continued on Cow's milk, Schizophrenia and Autism.

Saturday, 8 June 2013

Gizmag: Injectable nanoparticles maintain normal blood-sugar levels for up to 10 days.

Fascinating technology featured in Gizmag & posted by someone HERE.
The nano-network that releases insulin in response to changes in blood sugar
"The injectable nano-network is made up of a mixture that contains nanoparticles with a solid core or insulin, modified dextran (which is commonly used to reduce blood viscosity), and glucose oxidase enzymes. When exposed to high levels of glucose, the enzymes convert glucose into gluconic acid, which breaks down the modified dextran to release the insulin. The gluconic acid and dextran, which are biocompatible, dissolve in the body, while the insulin brings the glucose levels under control.

The nanoparticles are given a positively or negatively charged biocompatible coating so that when they are mixed together, they are attracted to each other to form a “nano-network.” The positively charged coatings are made of chitosan, a material found in shrimp shells that has also found applications in self-healing car paint, while the negatively charged coatings are made of alginate, a material normally found in seaweed."

Wow! Cool bananas!

Wednesday, 5 June 2013

When the only tool in the box is a hammer...

Everything that needs fixing looks like a nail.

People with diabetes mellitus are issued with blood glucose meters - and nothing else.

For people with type 1 diabetes, that's fine. They lack insulin, so they have to inject insulin in the right amounts & types to keep their blood glucose levels within reasonable limits. Applying Bernstein's Law of small numbers by reducing glycaemic load to a minimum keeps blood glucose levels within reasonable limits (between 3 & 7mmol/L) most of the time. See also The problem with Diabetes.

For people with type 2 diabetes and excessive visceral (belly) fat (~85% of people with type 2 diabetes), that's not fine. Their disease is a disease of chronic excess intake relative to oxidation, causing fasting dyseverythingaemia
(hyperglycaemia, hypercholesterolaemia, hyperNEFAaemia, hypertriglyceridaemia, hyperuricaemia, etc). People who have type 2 diabetes don't have only postprandial hyperglycaemia - they also have postprandial hypertriglyceridaemia. See Lifestyle Intervention Leading to Moderate Weight Loss Normalizes Postprandial Triacylglycerolemia Despite Persisting Obesity. Postprandial hypertriglyceridaemia is atherogenic. See Ultra-high-fat (~80%) diets: The good, the bad and the ugly.

However, because the only tool in the box of someone with type 2 diabetes is a blood glucose meter, their disease looks like one of only hyperglycaemia. Applying Bernstein's Law of small numbers by reducing carbohydrate intake to a minimum keeps blood glucose levels within reasonable limits, but makes other things worse if energy from carbohydrates is replaced by energy from fats.

Only if energy from carbohydrates is reduced AND energy from fats isn't increased to compensate (i.e. eat a LCLF PSMF or Modified PSMF until sufficient visceral fat has been lost), does carbohydrate restriction help people with type 2 diabetes.

Monday, 20 May 2013

Keep 'em tight, Part 2.

Keep 'em tight was about the ramifications of excessive gut permeability, a.k.a."Leaky Gut".
Graphic From: www.leakygutcure.com
Almost as an afterthought, I added to that post a link to Physiology and Immunology of Digestion. As this article is interesting & informative and since only 706 people have read the first post since it was published (the link was added quite some time later), I thought that I'd give it another airing, with a picture to make the post more attractive.

Saturday, 11 May 2013

Diabetes: which are the safest carbohydrates?

In my previous post, I stated that people with T2DM should eat ~150g/day of carbohydrate.
Soak & cook your own beans al-dente, for slowest release carbs.
See International table of glycemic index and glycemic load values: 2002. Below is a list of carbohydrates that have a low glycaemic load, or GL (GL = glycaemic index * grams of carbohydrate in the serving).


Non-nutritive sweeteners:


It's often claimed that non-nutritive sweeteners produce a cephalic phase insulin response. The mere anticipation of eating produces a cephalic phase insulin response. See How neural mediation of anticipatory and compensatory insulin release helps us tolerate food. An insulin response suppresses serum NEFAs, so it's not all bad.


Sugars and Sugar alcohols:


Fructose is not recommended for people with T2DM, as it "barges its way" into the liver via Glu-T5 and fructokinase. People with T2DM who have a high fasting serum glucose level almost certainly already have full liver glycogen stores, so adding to them isn't advisable. Whole fruits (not juices) are fine.
Lactose has a virtually zero GL, isn't very sweet and has/hasn't a laxative effect in large quantities (lactase-dependent). Heating lactose turns it into lactulose.
Lactulose has a virtually zero GI, is sweet and has a laxative effect in large quantities.
Galactose is not recommended, as large amounts may accelerate ageing.
D-mannose has a virtually zero GI, is sweet and doesn't have a laxative effect in large quantities. It can be used to treat urinary tract infections (UTIs) caused by e.coli, due to the fact that the kidneys filter it out of the blood and pass it out in the urine. Mannose in urine reduces the adhesion of e.coli to the inside wall of the urinary tract. See Intervening with urinary tract infections using anti-adhesives based on the crystal structure of the FimH-oligomannose-3 complex.
Trehalose has a virtually zero/moderate GI, is sweet and has/hasn't a laxative effect in large quantities (trehalase-dependent).

Lactitol has a virtually zero GI and has a laxative effect in large quantities.
Sorbitol has a virtually zero GI and has a laxative effect in large quantities.
Xylitol has a virtually zero GI, minty overtones and reduces dental plaque. However, it has a laxative effect in large quantities.
Erythritol has a virtually zero GI, minty overtones and is wee'ed-out like D-mannose, so it doesn't have a laxative effect in large quantities.


Starches:


Note: Tinned starches are usually overcooked, so cook your own. Don't overcook starches, as that makes them faster-absorbing. Al dente is best.

Gram dhal a.k.a. chana dal.
Long-grain rice. Refrigerating boiled rice for 24 hours lowers the GL, by forming resistant starch. See item 275 in the table in the first link.
New potatoes. Refrigerating boiled new potatoes for 24 hours lowers the GL a lot, by forming resistant starch. See item 605 in the table in the first link. You can boil old potatoes, but they're probably not as good.
Pearl barley.
Sweet corn.
Beans.
Chickpeas.
Lentils.
Peas.
Starchy nuts e.g. peanuts , cashews and chestnuts.
Vegetables.
Root vegetables.
Raw carrots.

If even low-GL carbs spike BG too much, this indicates severe IR in liver and/or skeletal muscle. See Insulin Resistance: Solutions to problems.

The above lists also apply to people with T1DM who are having difficulty keeping their blood glucose level between 3 and 7mmol/L.

Sunday, 31 March 2013

Doctor, every time I do *this*, it hurts!

The correct response is either:-

1) Go to hospital and get that broken finger fixed, or
2) Stop doing *that*!

There seem to be a lot of people out there who are having problems with wheat gluten (gliadin), casein and other proteins. As Matt Lalonde said in The Science Behind the Paleolithic Diet, some proteins are harder to digest than others.

Here's a hard to digest protein:-


It's raw albumin (egg white protein). As mentioned in As sure as Eggs is Eggs....., raw albumin is poorly absorbed, compared to cooked albumin. To digest the above protein requires peptidase enzymes (pepsin, trypsin and chymotrypsin) to break the peptide bonds. This has to be done from the outside inwards, so a large, heavily-folded protein takes a long time to break down into individual amino acids. Cooking albumin changes the 3-D structure - this is called denaturing. Cooked albumin digests much faster than raw albumin, which is why it's much better absorbed. Cooked proteins are generally faster to digest than raw proteins, unless they're burned to a crisp on a barbecue!

In a person with a healthy gut, partially-digested proteins are not absorbed, as the molecules are too large to pass through the tight junctions in the small intestine. They just ferment, producing malodorous wind. In a person with impaired gut permeability, partially-digested proteins pass through the loose junctions and get into the blood, provoking an immune response. This is not good, so Keep 'em tight.

People who suffer ill-effects after eating certain proteins may either have the wrong genes (e.g. coeliac disease), or have impaired gut permeability. The former isn't fixable but the latter may be. In the meantime, if eating "X" hurts, don't eat "X"!

Friday, 20 April 2012

How eating sugar & starch can lower your insulin needs.

This is a bookmarking post. Jason Sandeman is a chef who had a couple of web-sites at Well Done Chef! and Jason Sandeman — Real Food For Your Life. He has Latent Autoimmune Diabetes of Adulthood (LADA), which has resulted in a total loss of his pancreatic beta cells which means that he has to inject insulin.

Now, it's generally believed in low-carb circles (and by myself) that people with Type 1 Diabetes Mellitus (T1DM) should minimise their intake of sugary & starchy carbohydrates as these promote wild fluctuations in blood glucose. See The problem with Diabetes.

Jason wrote the following comment on Richard Nikoley's blog. The relevant part is as follows:-
"Even more weird – now that I have introduced the starches into the diet – I have actually got better control now. I thought my insulin needs would go up – but they haven’t. They’ve gone down."

To which I replied:-"How about this for an explanation? You now have a well-controlled glucose input to your circulation via diet, which has suppressed the poorly-controlled glucose input to your circulation via hepatic glucose production."

Hepatic glucose production (HGP) is increased by Glucagon, Cortisol & Adrenaline/Epinephrine. These are secreted as blood glucose level falls below certain values in order to keep our brains alive. See Blood Glucose, Insulin & Diabetes.

As keeping our brains alive is rather important (!), the mechanism is fairly crude in operation and blood glucose can overshoot in a positive direction, as a bit of glycation is less harmful than brain death. See "Funny turns": What they aren't and what they might be. Hyperglycaemia requires insulin to lower blood glucose back to the normal range.

Therefore, eating some (but not too much) sugar & starch can result in lower blood glucose level and lower insulin secretion. Eating fibre/fiber (a carbohydrate) is also good for keeping blood glucose low, as only just mentioned in Fiber and Insulin Sensitivity. Ain't the human body weird?"

Saturday, 25 February 2012

Cheapest Vitamin D3 yet.

A big thank you to Ted Hutchinson for bringing Vitamin D3 to my attention. Healthy Origins, Depot Vitamin D3, 125mcg (5,000IU) is very reasonably priced (£26.56 for 360 gelcaps which is a year's supply at 2026 prices).


Friday, 25 February 2011

"Funny turns": What they aren't and what they might be.

Sometimes, doing a large amount of high-intensity exercise while on a ketogenic diet can result in a "Funny turn", i.e. a weird feeling which may include sweating, dizziness & feeling faint.

The good news is that it's harmless, provided you don't faint, hit your head on something hard/sharp & fatally fracture your skull, or do it regularly. Stop and sit/lie down until the feeling passes. What's happening?

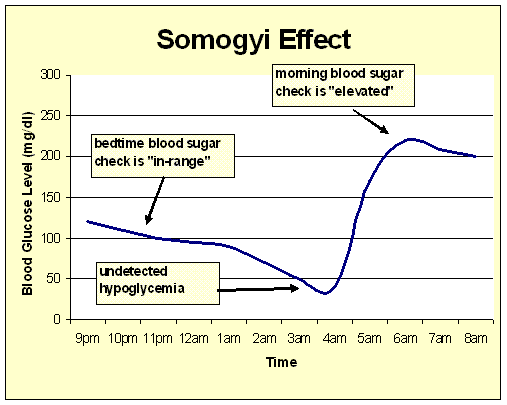
What isn't happening, is a Somogyi rebound. A Somogyi rebound happens when too much insulin is injected and it's bad because it results in rebound hyperglycaemia.


Did you know that there is insulin, insulin and insulin? According to Insulin: Degradation, "It has been estimated that an insulin molecule produced endogenously by the pancreatic beta cells is degraded within approximately one hour after its initial release into circulation (insulin half-life ~ 4–6 minutes)". According to Insulin: As a medication, injected insulin lingers in the blood for hours for fast-acting and days for slow-acting. This makes an overdose of injected insulin dangerous, as it can linger for long enough to cause fatal hypoglycaemia unless medical help is obtained.


What might be happening, is this: On a ketogenic diet, muscle glycogen stores are "trickle-charged" from blood glucose. High-intensity exercise oxidises muscle glycogen at a very rapid rate. See It's all in a day's work (as measured in Joules). Muscles can oxidise carbs at a rate of 4g per minute.

If muscle cells run out of stored glycogen, they become exquisitely sensitive to insulin and glucose importing processes are up-regulated. There is only ~4.5g of glucose in the blood at any given time, topped-up by the liver & kidneys and oxidised by the brain & red blood cells at a rate of less than 4g per hour (if keto-adapted). If muscles suddenly take up glucose at a rate of 4g per minute, blood glucose level can fall rapidly.

As dropping dead due to running for your life on very little or no food is bad, the body has several mechanisms for raising blood glucose.

From Blood Glucose, Insulin & Diabetes, "When BG falls to ~3.3mmol/L, the pituitary gland kicks-in and secretes ACTH (adrenocorticotropic hormone) which stimulates the release of cortisol from the adrenal cortex. Cortisol further stimulates gluconeogenesis in the liver & kidneys. When BG level falls to ~2mmol/L, the pituitary secretes GH (Growth Hormone) which has an anti-insulin effect." Adrenaline secretion increases, as adrenaline shifts fuel utilisation away from carbohydrate and towards fat. A sudden increase in the levels of adrenaline, cortisol & GH in the blood make you sweaty, dizzy & feel faint, so you stop exercising.

If it happens regularly, chronically-elevated adrenaline & cortisol levels result in you "falling apart" after about two years. See Survival of the Smartest (part 2) - Dr Diana Schwarzbein.

How come it's harmless? Glycogen-depleted & exquisitely insulin-sensitive muscles act as a natural blood glucose limiter because they draw in glucose so readily. There's no rebound hyperglycaemia.

This also reduces the "Dawn Phenomenon", another plus point for low-carb diets for people with T1D.

See also Can very-low-carb diets impair your mental faculties.

Tuesday, 1 February 2011

Keep 'em tight.

Wheel nuts? Nope!
Image from https://suppversity.blogspot.de/2012/11/shedding-some-light-on-the-leaky-gut.html
I'm referring to Tight Junctions. As mentioned at the end of Wheat? Oh, dear! , 10% of people who are healthy enough to donate blood have gut walls permeable enough to let gliadin fragments pass into the blood.

Tight junctions are important, as they keep the contents of the gut inside the gut and out of the blood. If you read Food Combining: What's THAT all about?, you'll see that during digestion, proteins are broken down into individual amino acids & very short peptide chains*. Amino acids & very short peptide chains are small enough to pass through tight junctions. Peptide chains longer than about 3 amino acids are too big to pass through. See also Physiology and Immunology of Digestion.

Carbohydrates are broken down into monosaccharides, which are small enough to pass through. Disaccharides are too large.

Fats are broken down into glycerol and fatty acids. Glycerol is small enough to pass through. Fatty acids and other fatty molecules such as Vitamin D, Co-enzyme Q10, Vitamin K2, curcumin, berberine etc are transported across.

The consequences of having loose junctions are not good. Chains of amino acids that aren't supposed to pass through the gut wall enter the body and produce an antibody response, e.g. Beta-CasoMorphin 7 and/or Gliadorphin 7. That in itself isn't a problem, unless amino acid sequences in the chains match amino acid sequences in certain parts of the body.

Diseases of autoimmune origin such as Coeliac disease (gut), Eczema (skin), Dermatitis herpetiformis (skin), Psoriasis (skin & joints), Sjögren's syndrome (mucous membranes), Cerebellar ataxia (Purkinje cells in the brain), Multiple sclerosis (myelin sheaths of nerves), Type 1 Diabetes (pancreatic beta cells), Rheumatoid arthritis (joints), Asthma (lungs), Lupus erythematosus (various), Autoimmune thyroiditis (thyroid), LADA (pancreatic beta cells) etc are caused by antibody responses inappropriately attacking parts of the body. Autoimmune diseases can also occur after bacterial & viral infections.

The other day, I found Immune response to dietary proteins, gliadin and cerebellar peptides in children with autism.

See also Stronger Intestinal Barrier May Prevent Cancer in the Rest of the Body, New Study Suggests.

So, how do we keep 'em tight? See Vitamin D.
See also Dietary Fat Can Modulate Intestinal Tight Junction Integrity.
See also Shedding Some Light on the Leaky Gut <> Exercise Connection. Plus: 20+ Things You Should or Shouldn't Do to Protect and Restore the Integrity of Your Intestinal Wall.
See also Sulphation and Autism: What are the links? A good source of sulphate is Epsom Salts.


In other news....
I had a phone call from mum's GP this morning. Having read my evidence, he's agreed to test mum's serum B12, 25(OH)D and Calcium and give her supplements accordingly. He's also happy with me giving mum a Ketogenic diet and will also advise the nursing home to exercise mum as often as she is able. Result!

I put four cubes of liver pâté out for Sooty & Sweep (I don't know which one is which as they're identical) and a Magpie swiped two of them. We also have seagulls. I put the other two cubes out of sight in a box.


So far, so good!

P.S. What fuel can be extracted from decomposing seagulls?
.
.
.
Wait for it...
.
.
.
Petrel! (From Petrol Direct, a joke site in case anyone's wondering).

Thursday, 25 March 2010

Vitamin D3: Studies from 2005 to present.

I had a rummage through PubMed looking for editorials, meta-studies & human Randomised Controlled Trials on Vitamin D and Vitamin D3 from 2005 to present. Here is a selection (mostly using reasonable doses) that weren't previously mentioned in my Vitamin D blog. They are, now!

The Role of Vitamin D in Cancer Prevention
Estimates of optimal vitamin D status.
Prevalence of Vitamin D inadequacy among postmenopausal North American women receiving osteoporosis therapy.
Fracture prevention with vitamin D supplementation: a meta-analysis of randomized controlled trials.
The re-emerging burden of rickets: a decade of experience from Sydney.
An excess of widespread pain among South Asians: are low levels of vitamin D implicated?
Vitamin D is associated with improved survival in early-stage non-small cell lung cancer patients.
Vitamin D and prevention of colorectal cancer.
Should older people in residential care receive vitamin D to prevent falls? Results of a randomized trial.
Effect of vitamin D replacement on musculoskeletal parameters in school children: a randomized controlled trial.
Effect of cholecalciferol plus calcium on falling in ambulatory older men and women: a 3-year randomized controlled trial.
Vitamin D supplementation improves cytokine profiles in patients with congestive heart failure: a double-blind, randomized, placebo-controlled trial.
Estimation of optimal serum concentrations of 25-hydroxyvitamin D for multiple health outcomes.
Risk factors for vitamin D inadequacy among women with osteoporosis: an international epidemiological study.
A system for improving vitamin D nutrition in residential care.
Impact of dietary and lifestyle on vitamin D in healthy student girls aged 11-15 years.
How much vitamin D3 do the elderly need?
Lower levels of plasma 25-hydroxyvitamin D among young adults at diagnosis of autoimmune type 1 diabetes compared with control subjects: results from the nationwide Diabetes Incidence Study in Sweden (DISS).
A meta-analysis of second cancers after a diagnosis of nonmelanoma skin cancer: additional evidence that solar ultraviolet-B irradiance reduces the risk of internal cancers.
Risk assessment for vitamin D.
Supplementation with calcium + vitamin D enhances the beneficial effect of weight loss on plasma lipid and lipoprotein concentrations.
Serum 25(OH)D levels, dietary intake of vitamin D, and colorectal adenoma recurrence.
The effects of calcium and vitamin D supplementation on blood glucose and markers of inflammation in nondiabetic adults.
Optimal vitamin D status for colorectal cancer prevention: a quantitative meta analysis.
A higher dose of vitamin d reduces the risk of falls in nursing home residents: a randomized, multiple-dose study.
Potentially modifiable determinants of vitamin D status in an older population in the Netherlands: the Hoorn Study.
Fracture prevention with vitamin D supplementation: considering the inconsistent results.
A prospective study of plasma vitamin D metabolites, vitamin D receptor polymorphisms, and prostate cancer.
The role of vitamin D and calcium in type 2 diabetes. A systematic review and meta-analysis.
A single dose of vitamin D enhances immunity to mycobacteria.
Does solar exposure, as indicated by the non-melanoma skin cancers, protect from solid cancers: vitamin D as a possible explanation.
Vitamin D intake and breast cancer risk in postmenopausal women: the Iowa Women's Health Study.
Vitamin D and calcium supplementation reduces cancer risk: results of a randomized trial.
Bone mineral density and bone markers in patients with a recent low-energy fracture: effect of 1 y of treatment with calcium and vitamin D.
Vitamin D deficiency in multicultural primary care: a case series of 299 patients.
Vitamin D supplementation and total mortality: a meta-analysis of randomized controlled trials.
Efficacy of different doses and time intervals of oral vitamin D supplementation with or without calcium in elderly nursing home residents.
Vitamin D status and response to Vitamin D(3) in obese vs. non-obese African American children.
Vitamin D and skin physiology: a D-lightful story.
Additive benefit of higher testosterone levels and vitamin D plus calcium supplementation in regard to fall risk reduction among older men and women.
Rapid correction of low vitamin D status in nursing home residents.
Effects of a long-term vitamin D and calcium supplementation on falls and parameters of muscle function in community-dwelling older individuals.
Prevalence of vitamin d insufficiency in patients with Parkinson disease and Alzheimer disease.
Exploration of association of 1,25-OH2D3 with augmentation index, a composite measure of arterial stiffness.
Vitamin D and prevention of colorectal adenoma: a meta-analysis.
The tolerability and biochemical effects of high-dose bolus vitamin D2 and D3 supplementation in patients with vitamin D insufficiency.
Administration of oral vitamin D induces cathelicidin production in atopic individuals.
Estimation of the dietary requirement for vitamin D in healthy adults.
Changes in 25-Hydroxyvitamin D3 to oral treatment with vitamin D3 in postmenopausal females with osteoporosis.
Vitamin D or hormone D deficiency in autoimmune rheumatic diseases, including undifferentiated connective tissue disease.
High-dose oral vitamin D3 supplementation in the elderly.
A double-blind, randomized, placebo-controlled trial of the short-term effect of vitamin D3 supplementation on insulin sensitivity in apparently healthy, middle-aged, centrally obese men.
Vitamin D deficiency in older men.
Serum vitamin D and risk of pancreatic cancer in the prostate, lung, colorectal, and ovarian screening trial.
Vitamin D supplementation during Antarctic winter.
Vitamin D insufficiency and treatment with oral vitamin D3 in northern-dwelling patients with chronic kidney disease.
Long-term effects of giving nursing home residents bread fortified with 125 microg (5000 IU) vitamin D(3) per daily serving.
Effects of vitamin D and calcium supplementation on markers of apoptosis in normal colon mucosa: a randomized, double-blind, placebo-controlled clinical trial.
Estimation of the dietary requirement for vitamin D in free-living adults >=64 y of age.
Vitamin D supplementation enhances the beneficial effects of weight loss on cardiovascular disease risk markers.
Plasma 25-hydroxyvitamin D concentration and metabolic syndrome among middle-aged and elderly Chinese individuals.
Meta-analysis: longitudinal studies of serum vitamin D and colorectal cancer risk.
Effect of vitamin D supplementation in the institutionalized elderly.
Calcitriol ointment 3 microg/g is safe and effective over 52 weeks for the treatment of mild to moderate plaque psoriasis.
Association between 25-hydroxyvitamin D levels and cognitive performance in middle-aged and older European men.
Low parathyroid hormone levels in bedridden geriatric patients with vitamin D deficiency.
Increased levels of 25 hydroxyvitamin D and 1,25-dihydroxyvitamin D after rosuvastatin treatment: a novel pleiotropic effect of statins?
Effect of vitamin D deficiency and replacement on endothelial function in asymptomatic subjects.
Vitamin D and depressive symptoms in women during the winter: a pilot study.
Treatment of vitamin D deficiency increases lower limb muscle strength in institutionalized older people independently of regular physical activity: a randomized double-blind controlled trial.
Vitamin D, parathyroid hormone and the metabolic syndrome in middle-aged and older European men.
Vitamin D supplementation reduces insulin resistance in South Asian women living in New Zealand who are insulin resistant and vitamin D deficient - a randomised, placebo-controlled trial.
Fall prevention with supplemental and active forms of vitamin D: a meta-analysis of randomised controlled trials.
Meta-analysis of vitamin D, calcium and the prevention of breast cancer.
Effects of vitamin d and calcium on proliferation and differentiation in normal colon mucosa: a randomized clinical trial.
Combination of alfacalcidol with calcium can improve quadriceps muscle strength in elderly ambulatory Thai women who have hypovitaminosis D: a randomized controlled trial.
Vitamin D(3) induces expression of human cathelicidin antimicrobial peptide 18 in newborns.
Levels of vitamin D and cardiometabolic disorders: systematic review and meta-analysis.
No significant effect on bone mineral density by high doses of vitamin D3 given to overweight subjects for one year.
Effects of supplemental vitamin D and calcium on oxidative DNA damage marker in normal colorectal mucosa: a randomized clinical trial.
Vitamin D levels, lung function, and steroid response in adult asthma.
Association between pre-diagnostic circulating vitamin D concentration and risk of colorectal cancer in European populations:a nested case-control study.
Pandemic preparedness for swine flu influenza in the United States.
Randomized trial of vitamin D supplementation to prevent seasonal influenza A in schoolchildren.
Vitamin D supplementation suppresses age-induced bone turnover in older women who are vitamin D deficient.
Suppression of C-terminal telopeptide in hypovitaminosis D requires calcium as well as vitamin D.
A phase I/II dose-escalation trial of vitamin D3 and calcium in multiple sclerosis.
Milk fortified with the current adequate intake for vitamin D (5 microg) increases serum 25-hydroxyvitamin D compared to control milk but is not sufficient to prevent a seasonal decline in young women.
Vitamin D-vitamin K interaction: effect of vitamin D supplementation on serum percentage undercarboxylated osteocalcin, a sensitive measure of vitamin K status, in Danish girls.
Vitamin D status and impact of vitamin D3 and/or calcium supplementation in a randomized pilot study in the Southeastern United States.
Calcium/vitamin D supplementation and coronary artery calcification in the Women's Health Initiative.
Circulating 25-hydroxyvitamin D and risk of pancreatic cancer: Cohort Consortium Vitamin D Pooling Project of Rarer Cancers.*
A 16-week randomized clinical trial of 2000 international units daily vitamin D3 supplementation in black youth: 25-hydroxyvitamin D, adiposity, and arterial stiffness.
The effect of narrowband UV-B treatment for psoriasis on vitamin D status during wintertime in Ireland.
Effects of vitamin D supplementation to children diagnosed with pneumonia in Kabul: a randomised controlled trial.
Dairy calcium intake, serum vitamin D, and successful weight loss.
Atorvastatin increases 25-hydroxy vitamin D concentrations in patients with polycystic ovary syndrome.
A randomized controlled trial of the effects of vitamin D on muscle strength and mobility in older women with vitamin D insufficiency.
Serum 25-hydroxyvitamin D concentration is associated with functional capacity in older adults with heart failure.
Effect of vitamin D supplementation on testosterone levels in men.
Vitamin D production depends on ultraviolet-B dose but not on dose rate: a randomized controlled trial.
Vitamin D(3) is more potent than vitamin D(2) in humans.
Nutrients and foods for the primary prevention of asthma and allergy: systematic review and meta-analysis.
High-dose vitamin D(3) during intensive-phase antimicrobial treatment of pulmonary tuberculosis: a double-blind randomised controlled trial.
Circulating 25-hydroxyvitamin D levels and frailty in older men: the osteoporotic fractures in men study.
Association of low serum 25-hydroxyvitamin D levels and mortality in the critically ill.
Effects of vitamin D supplementation on 25-hydroxyvitamin D, high-density lipoprotein cholesterol, and other cardiovascular disease risk markers in subjects with elevated waist circumference.
Changes in balance, functional performance and fall risk following whole body vibration training and vitamin D supplementation in institutionalized elderly women. A 6 month randomized controlled trial.
Diet induced thermogenesis, fat oxidation and food intake following sequential meals: influence of calcium and vitamin D.
The response of elderly veterans to daily vitamin D3 supplementation of 2,000 IU: a pilot efficacy study.
Meta-analysis: Circulating vitamin D and ovarian cancer risk.
Relation of vitamin D level to maximal oxygen uptake in adults.
Vitamin D status in patients with stage IV colorectal cancer: findings from Intergroup trial N9741.
Circulating levels of vitamin D and colon and rectal cancer: the Physicians' Health Study and a meta-analysis of prospective studies.
Burning daylight: balancing vitamin D requirements with sensible sun exposure.
Relationships between vitamin D status and cardio-metabolic risk factors in young European adults.
Latitude is significantly associated with the prevalence of multiple sclerosis: a meta-analysis.
Vitamin D status and early age-related macular degeneration in postmenopausal women.
Vitamin D and clinical disease progression in HIV infection: results from the EuroSIDA study.
Annual high-dose vitamin D3 and mental well-being: randomised controlled trial.
Vitamin D status and outcomes in heart failure patients.
The impact of vitamin D status on periodontal surgery outcomes.
The role of paricalcitol on proteinuria.
Effects of weight loss on serum vitamin D in postmenopausal women.
Vitamin D status and mortality risk in CKD: a meta-analysis of prospective studies.
Vitamin D intake and risk of cardiovascular disease in US men and women.
Meta-analysis: Serum vitamin D and colorectal adenoma risk.
Calcium plus vitamin D supplementation and the risk of nonmelanoma and melanoma skin cancer: post hoc analyses of the women's health initiative randomized controlled trial.
Effects of vitamin D and calcium supplementation on pancreatic β cell function, insulin sensitivity, and glycemia in adults at high risk of diabetes: the Calcium and Vitamin D for Diabetes Mellitus (CaDDM) randomized controlled trial.
Vitamin D supplementation for prevention of mortality in adults.
The effect of calcium plus vitamin D on risk for invasive cancer: results of the Women's Health Initiative (WHI) calcium plus vitamin D randomized clinical trial.
New clinical trials with vitamin D and analogs in renal disease.
The relation between vitamin D deficiency and fibromyalgia syndrome in women.
Interventions for latent autoimmune diabetes (LADA) in adults.
Calcium and vitamin D supplementation is associated with decreased abdominal visceral adipose tissue in overweight and obese adults.
Effect of vitamin D supplementation on muscle strength, gait and balance in older adults: a systematic review and meta-analysis.
Vitamin D3 and the risk of CVD in overweight and obese women: a randomised controlled trial.
Low 25-hydroxyvitamin D is associated with increased mortality in female nursing home residents.
Improvement of vitamin D status resulted in amelioration of biomarkers of systemic inflammation in the subjects with type 2 diabetes.
Vitamin D supplementation in infants with chronic congestive heart failure.
Vitamin D reduces musculoskeletal pain after infusion of zoledronic acid for postmenopausal osteoporosis.
Consumption of vitamin D-and calcium-fortified soft white cheese lowers the biochemical marker of bone resorption TRAP 5b in postmenopausal women at moderate risk of osteoporosis fracture.
Vitamin D improves viral response in hepatitis C genotype 2-3 naïve patients.
Vitamin D supplementation in the treatment of atopic dermatitis: a clinical trial study.
Effect of vitamin D repletion on urinary calcium excretion among kidney stone formers.
25-Hydroxyvitamin D levels and the risk of stroke: a prospective study and meta-analysis.
Improvement of vitamin D status via daily intake of fortified yogurt drink either with or without extra calcium ameliorates systemic inflammatory biomarkers, including adipokines, in the subjects with type 2 diabetes.
Treatment of vitamin D insufficiency in children and adolescents with inflammatory bowel disease: a randomized clinical trial comparing three regimens.
Therapeutic effects of calcium & vitamin D supplementation in women with PCOS.
Higher vitamin D dietary intake is associated with lower risk of alzheimer's disease: a 7-year follow-up.
Vitamin D3 supplementation at 4000 international units per day for one year results in a decrease of positive cores at repeat biopsy in subjects with low-risk prostate cancer under active surveillance.
Comparison of narrowband ultraviolet B exposure and oral vitamin D substitution on serum 25-hydroxyvitamin D concentration.
The relation between sunscreen layer thickness and vitamin D production after ultraviolet B exposure: a randomized clinical trial.
Circulating 25-hydroxyvitamin D concentration and the risk of type 2 diabetes: results from the European Prospective Investigation into Cancer (EPIC)-Norfolk cohort and updated meta-analysis of prospective studies.
Vitamin D3 therapy corrects the tissue sensitivity to angiotensin ii akin to the action of a converting enzyme inhibitor in obese hypertensives: an interventional study.
The effect of combined calcium and cholecalciferol supplementation on bone mineral density in elderly women with moderate chronic kidney disease.
Comparison of vitamin D2 and vitamin D3 supplementation in raising serum 25-hydroxyvitamin D status: a systematic review and meta-analysis.
Relative effectiveness of oral 25-hydroxyvitamin D3 and vitamin D3 in raising wintertime serum 25-hydroxyvitamin D in older adults.
Vitamin D supplementation and depression in the women's health initiative calcium and vitamin D trial.
Vitamin D with calcium reduces mortality: patient level pooled analysis of 70,528 patients from eight major vitamin D trials.
An open label, randomized controlled study of oral calcitriol for the treatment of proteinuria in patients with diabetic kidney disease.
Ergocalciferol from mushrooms or supplements consumed with a standard meal increases 25-hydroxyergocalciferol but decreases 25-hydroxycholecalciferol in the serum of healthy adults.
Narrowband ultraviolet B three times per week is more effective in treating vitamin D deficiency than 1600 IU oral vitamin D₃ per day: a randomized clinical trial.
Vitamin D intake is inversely related to risk of developing metabolic syndrome in African American and white men and women over 20 y: the Coronary Artery Risk Development in Young Adults study.
Vitamin D and gestational diabetes: a systematic review and meta-analysis.
Associations between 25-hydroxyvitamin D and weight gain in elderly women.
Effect of cholecalciferol as adjunctive therapy with insulin on protective immunologic profile and decline of residual β-cell function in new-onset type 1 diabetes mellitus.
A pooled analysis of vitamin D dose requirements for fracture prevention.
Determinants and effects of vitamin D supplementation on serum 25-hydroxy-vitamin D levels in patients with rheumatoid arthritis.
Vitamin D is a major determinant of bone mineral density at school age.
Effect of vitamin D and inhaled corticosteroid treatment on lung function in children.
Serum 25-hydroxyvitamin D3 and D2 and non-clinical psychotic experiences in childhood.
Vitamin D deficiency in postmenopausal, healthy women predicts increased cardiovascular events: a 16-year follow-up study.
Randomized trial of vitamin D supplementation and risk of acute respiratory infection in Mongolia.
25-hydroxyvitamin d levels and risk of ischemic heart disease, myocardial infarction, and early death: population-based study and meta-analyses of 18 and 17 studies.
Association of low serum 25-hydroxyvitamin D levels and acute kidney injury in the critically ill.
A 12-week double-blind randomized clinical trial of vitamin D₃ supplementation on body fat mass in healthy overweight and obese women.
Circulating 25-hydroxy-vitamin D and risk of cardiovascular disease: a meta-analysis of prospective studies.
Relation of severe deficiency of vitamin D to cardiovascular mortality during acute coronary syndromes.
Vitamin D reduces left atrial volume in patients with left ventricular hypertrophy and chronic kidney disease.
Interventions for preventing falls in older people in care facilities and hospitals.
Vitamin D and risk of death from vascular and non-vascular causes in the Whitehall study and meta-analyses of 12,000 deaths.
Calcium plus vitamin D3 supplementation facilitated fat loss in overweight and obese college students with very-low calcium consumption: a randomized controlled trial.
Randomized controlled trial of vitamin D supplement on endothelial function in patients with type 2 diabetes.
Effect of vitamin D supplementation on progression of knee pain and cartilage volume loss in patients with symptomatic osteoarthritis: a randomized controlled trial.
Lipoprotein lipase links vitamin D, insulin resistance, and type 2 diabetes: a cross-sectional epidemiological study.
The effect of different doses of vitamin D supplementation on insulin resistance during pregnancy.
Vitamin D and dental caries in controlled clinical trials: systematic review and meta-analysis.
Vitamin D deficiency and depression in adults: systematic review and meta-analysis.
Improving the vitamin D status of vitamin D deficient adults is associated with improved mitochondrial oxidative function in skeletal muscle.
Low 25-OH vitamin D is associated with benign prostatic hyperplasia.
Correcting vitamin D insufficiency improves insulin sensitivity in obese adolescents: a randomized controlled trial.
Vitamin D levels in Alzheimer's and Parkinson's diseases: a meta-analysis.
Supplemental vitamin D and physical performance in COPD: a pilot randomized trial.
Vitamin D and risk of future hypertension: meta-analysis of 283,537 participants.
Randomized clinical trial of vitamin D3 doses on prostatic vitamin D metabolite levels and ki67 labeling in prostate cancer patients.
Randomized, double-blind, placebo-controlled trial of vitamin D supplementation in Parkinson disease.
Anti-inflammatory effect of vitamin D on gingivitis: a dose-response randomised control trial.
Role of vitamin D in children with respiratory tract infection.
Effect of vitamin D supplementation and ultraviolet B exposure on serum 25-hydroxyvitamin D concentrations in healthy volunteers: a randomized, crossover clinical trial.
Vitamin D and multiple sclerosis: what is the clinical impact?
Is hypovitaminosis D associated with abdominal aortic aneurysm, and is there a dose-response relationship?
Plasma vitamin D levels, menopause, and risk of breast cancer: dose-response meta-analysis of prospective studies.
Impact of vitamin D on chronic kidney diseases in non-dialysis patients: a meta-analysis of randomized controlled trials.
Serum 25-hydroxyvitamin D levels and the risk of depression: a systematic review and meta-analysis.
The effect of vitamin D-related interventions on multiple sclerosis relapses: a meta-analysis.
Vitamin D status and physical function in nursing home residents: a 1-year observational study.
Maternal vitamin D status and risk of pre-eclampsia: a systematic review and meta-analysis.
Meta-analysis: vitamin D and non-alcoholic fatty liver disease.
Serum 25-hydroxyvitamin D and breast cancer risk: a meta-analysis of prospective studies.
Treatment with oral active vitamin D is associated with decreased risk of peritonitis and improved survival in patients on peritoneal dialysis.
Vitamin D supplementation affects serum high-sensitivity C-reactive protein, insulin resistance, and biomarkers of oxidative stress in pregnant women.
The role of vitamin D supplementation in the risk of developing pneumonia: three independent case-control studies.
Short-term vitamin D3 supplementation lowers plasma renin activity in patients with stable chronic heart failure: an open-label, blinded end point, randomized prospective trial (VitD-CHF trial).
Vitamin D and psychosis: mini meta-analysis.
Meta-analysis of memory and executive dysfunctions in relation to vitamin D.
Vitamin D intake and lung cancer risk in the Women's Health Initiative.
Association of low serum 25-hydroxyvitamin D levels and sepsis in the critically ill.
Vitamin D favorably alters the cancer promoting prostaglandin cascade.
Vitamin D intake and risk of type 1 diabetes: a meta-analysis of observational studies.
Effect of vitamin D supplementation on antibiotic use: a randomized controlled trial.
Effects of vitamin D supplementation on glucose metabolism, lipid concentrations, inflammation, and oxidative stress in gestational diabetes: a double-blind randomized controlled clinical trial.
Improvement in high-density lipoprotein cholesterol levels in argentine Indian school children after vitamin D supplementation.
Vitamin D supplementation for prevention of mortality in adults.
Beneficial role for supplemental vitamin D3 treatment in chronic urticaria: a randomized study.
Vitamin D3 supplementation during weight loss: a double-blind randomized controlled trial.
Vitamin D and risk of cause specific death: systematic review and meta-analysis of observational cohort and randomised intervention studies.


*See Vitamin D and UV fluctuations for an explanation.

Phew! That's a bit more than I expected.

If you fancy doing a search yourself, click on PubMed.